A collection of complex joint preservation and replacement case studies and random thoughts of a orthopedic surgeon essentially aimed at knowledge dissemination.
Sunday, 15 April 2018
superior capsular reconstruction
post op 3 months thanks to physio Sreejith's efforts post op
painful dislocated rt shoulder in a 76 year old lady
Mri showed chronic cuff tear grade 3 gautilier
with subscap tear
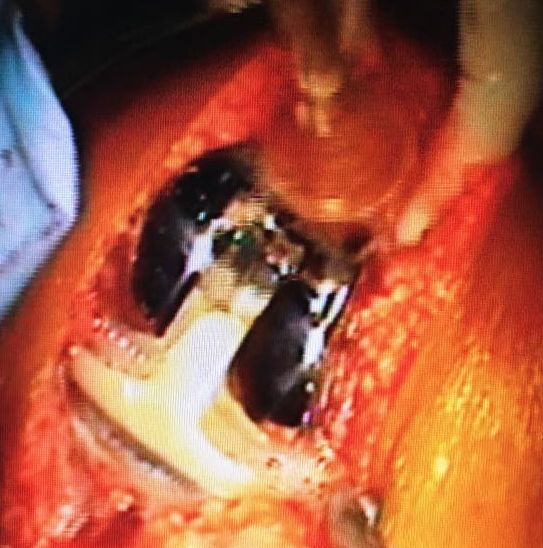
The issue of reverse shoulder was easy as she has pain and was unstable due to cuff tear arthropathy with thrice weekly dislocation during sleep. Before the arrival of Grammonts prosthesis, fusion could have been the only option
The next problem whether a constrained liner was needed or a subscap repair was mandatory or desirable. In this case as subs cap was retracted further to try repair a constrained liner was use and the result is below


Saturday, 13 January 2018
6 year post hybrid technique in rt periprosthetic fracture femur
The rt hip under went distal cementing and proximal uncemented in a 80 year old lady who presented 6 years later with no local issues in the hip. This was considered a quick operation for an elderly peri prosthetic fracture for early mobilisation with an uncememeted hip. the porocoat distally was removed to reduce the stem cement bonding.Happy to see no major lysis or sinkage 6 years down the line
posterior dislocation 2 year post posterior stabilised knee
This happenned while she was getting up from a foot stool like devise ( possible high flexion). felt a clunk and could not walk. presented with an FFD of 30 with no further flexion or extension with xray below showing subluxed knee.
Under GA it reduced in full flexion and anterior force ie anterior draw and was stable with no further instabilty or laxity, no clinical laxity in any range. This was the first time I saw this and hope fully the last time. so watch out high flexion guys who show videos of squats and more ? She is 6 months post reduction with no further issues yet
Monday, 20 November 2017
meniscal repalcement
26 yr old male with 2 year post acl tear medial meniscal was in bits except an intact root and a peripheral rim was intactInspite of ACL a reconstruction the evidence of impending osteoarthritis made us consider a meniscal replacement when transplant was unavailable. He is two year post op with no symptoms to date recent mri shows still some tissue perisisting although smaller than immediate postop

Monday, 19 December 2016
nail plate devise
An
out line on the design and rationale of the nail plate device
for stabilising a periprosthetic fracture of distal femur in total knee
replacement-
Dr. Jacob Varughese
Displaced supracondylar fractures (type 2) needs to be properly
aligned and stabilized for an optimal outcome. Stabilization using
intramedullary nails, locking plates, external fixators have been
described. The small porotic distal fragment precludes stable fixation with either plate or nail to commence immediate mobilisation.
Design of a nail plate device
In 2009 following
difficulty in stabilising these distal femoral fractures combination of a separate Intra medullary nail and a locking plate was used to stabilise and mobilise the elderly
above mentioned osteoporotic fracture.
This was repeated in bilateral case where in the nail was
removed to pass the distal locking
screws from the plate resulting in
translation of the distal fragment ref
pic 4 below. Both the fractures healed in 3 months and the
patient was mobilised weigth bearing
Procedure
Knee replacement
incision.
A supracondylar nail 9 mm in diameter was passed through the distal
fragment and using this to reduce the
fragment and pass it retrograde into the proximal fragment. This avoids soft
tissue stripping and quick reduction of the fracture in anterior-posterior and
medial lateral planes with out soft
tissue stripping associated with reduction with a plate device. This nail
devise could be locked proximally and distally if possible or at this stage a
locking plate is passed through a MIPPO technique on the lateral side and
locking screws can be applied distally though the incision and percutaneous
screws can be applied proximally. In the case
in picture 3 on the right knee the nail was removed after the plate was
applied distally to facilitate screw
insertion resulting in translation in the medio-lateral plane. Therefore it was
decided to use both nail and plate in 3 further cases where in we obtained
stable reduction to facilitate immediate mobilisation.
With these results we attempted to design a
new implant ( nail plate device) to improve the technique and rigidity of fixation
hybrid technique in periprosthetic femoral fractures
This patient had cementing of the distal half of the uncemented porocoat stem with wiring around the proximal uncemented part for a periprosthetic fracture 6 years ago
Doing well so far with no lysis so far
I did expect loosening on the cement bone interface but luckily no lysis so far
so this is an option in a elderly periprosthetic fracture
similar case below
http://knee-replacement-india.blogspot.in/2009/12/perprosthetic-fracture-in-octogenarian.html
Wednesday, 30 November 2016
Root tears of meniscus
60 year old lady with sudden onset sharp pain lt knee. She was previously asymptomatic and very active. clinical exam revealed strong medial meniscal signs and MRI showed a meniscal extrusion with radial tear adjacent to root.
she was send for a week of physio and 3 days of NSAID and was reviewed . she had complete relief and had no meniscal signs and was even able to squat
After repairing every root tear I saw I sometimes think whether I over did the same. Meniscal extrusion remained in at least 3 of the 12 1 repaired in the last 2 years. Pt were definitely asymptomatic.
To avoid extrusion do we now need to start centralisation sutures like the japs.
Spare a thought guys.
POPLITIOMENISCAL FASCICLE TEARS
Did we miss this injury in the past. The fascicle move the lateral meniscus dynamically during the lateral femoral condyle roll back. one needs to repair it all inside or with a suture lasso as shown in arthroscopic techniques. to diagnose the same on mri is sometimes difficult.
Pt complaints of a pop sound or locking.
Laprade figure or four test yield is negligible in my hands so far
most accurate diagnosis is introp, the meniscus can be displaced anteriorly by more than 50% of its width . one might see some chondral defect adjoining to the popliomeniscal fascicle deep to the meniscal
one could use a mid lateral portal to repair the same
Friday, 28 October 2016
use of constained TKR implants in BMI above 40
After seeing a small series of delayed mcl injuries in high flexion, high BMI TKRs and similar issues in published in arthroplasy journal ie; 12 percent in high bmi series in my thoughts and solutions changed
In heavy individuals I would use stems and varus/valgus constraint devise to
1.To decrease stress at the implant cement and bone interphase
2.To avoid stress on the MCL whose delayed ruptures are reported in high BMI individual
3.To ?? reduce anterior subluxation of the tibia in flexion past 70 degrees when the calf and thigh meet and creating an anterior vector ( do we need a anterior and posterior stabilised implant here (food for thougth)
I
used the Exprt
revision knee implant(DJO) with vit E poly insert as this is the only constrained system where Vit E poly is available where in one can hopefully reduce wear
They have a simplified 2 tray revision system which reduces the complexity of revision surgery Iin OR to
reduce errors if the defects are not huge.
Sunday, 31 January 2016
medical management of osteoarthrosis
The basic science guys have been working hard to help reduce the osteoarthritis disease burden. Every week a new possible solution is talked about. From microbiomes to ginger, ,curcumin,
Intra articular human lubricin Inj to glucosamine with NAPA to reduce cartilage degeneration
The FDA approval of mri as a tool to asses disease progression for trials will open up research and pace of new disease modifying drugs appearance in the market will increase. hopefully the quaks will get exposed. With MOCART 2 grading the results can be better evaluated.
Saturday, 13 June 2015
is repair better than reconstruction on the medial side in MLKI 3m injuries
The results of medial repair did better than reconstructions in my series so far. In the lateral and plri reconstructions gave near normal results. This was discussed with few of panel of experts privately at the ISAKOS. Few disagreed with my view. my reconstructions have been with semitendinosis and not tendon Achilles which is broader.
1. Did this alter the results?
2. Is it because poplitius is intra articular while mcl is extra articular ?
3. Is it because of the adhesions between the layers of the medial bursa?
used LAD in 2 cases so far on the medial side repairs with good results so far
Do others agree with my comments or have a other experience
Friday, 7 November 2014
Thursday, 30 October 2014
thr in acetabular fracture
38 yr old 2 yrs post acetabular fracture and supracondylar fracture presented with pain and stiffness. no free movements plan was to remove proximal femoral screws and any acetabular screws interfering with the cup
1 . retained implants
2.infection
3.deformed acetabulum
3.nonunion with dissociation or resorption
4.cavitatory or segmental defects
5.HO
6.neurological deficit
7. Impaired musculature
if you asses the results one can find the following
symptomatic acetabular loosening is higher
uncemented cups do better at medium term.
neurological defecits, HO are higher. Cavitatory defect can be filled with morcelised bone grafts and impacted or reverse reamed. Majority host bone contact should be at least 70 percent if possible specially in the wt bearing zone. Avoid large grafts as they do not revascualrise completely and might fail in the medium term. In case of dissociation cage cup combo bypassing the defect would give reasonable 10 year results. Recently distraction of the dissociation stabilized by cup reinforced by cage and a cemented cup has been proposed and published by paprosky

templating done by Dr. kattab who is my colleague
The two independent screws were intraarticular transfixing the head which had to osteotomised in situ. and a primary ceramic on ceramic hip was done. introp frozen section and cultures were taken/
1 . retained implants
2.infection
3.deformed acetabulum
3.nonunion with dissociation or resorption
4.cavitatory or segmental defects
5.HO
6.neurological deficit
7. Impaired musculature
if you asses the results one can find the following
symptomatic acetabular loosening is higher
uncemented cups do better at medium term.
neurological defecits, HO are higher. Cavitatory defect can be filled with morcelised bone grafts and impacted or reverse reamed. Majority host bone contact should be at least 70 percent if possible specially in the wt bearing zone. Avoid large grafts as they do not revascualrise completely and might fail in the medium term. In case of dissociation cage cup combo bypassing the defect would give reasonable 10 year results. Recently distraction of the dissociation stabilized by cup reinforced by cage and a cemented cup has been proposed and published by paprosky
Subscribe to:
Posts (Atom)